What Do CPS and TPS Scores Mean in a PD-L1 Test? How Do Staining Rates Affect Things?
In this article
Reading the Numbers on Your PD-L1 Report: A Guide to TPS, CPS and Cutoff Values
Many patients for whom immunotherapy is being considered find lines such as "PD-L1 (22C3): TPS 60%" or "CPS 15" in their pathology report. These numbers show the proportion of cells in the tumor tissue that carry a protein called PD-L1. TPS (tumor proportion score) counts only tumor cells, whereas CPS (combined positive score) counts tumor cells together with the surrounding immune cells. As the staining rate rises, the likelihood of benefiting from drugs that target PD-1 and PD-L1 generally increases; for this reason, in many cancers these cutoffs determine who receives immunotherapy and whether it is given alone or together with chemotherapy. PD-L1 is not a perfect test, however: which score is used and which cutoff applies vary by cancer type, drug and country. In this guide, we explain how the two scores are calculated, which cutoff is used in which cancer, and what can change your result. We covered the basics of immunotherapy in our article on pembrolizumab (Keytruda) and another biomarker used in immunotherapy in our guide to tumor mutational burden (TMB).
- What is TPS? It is the proportion of PD-L1-stained tumor cells among all viable tumor cells, reported as a percentage. It is used mainly in non-small cell lung cancer, where ≥50% is considered "high," 1–49% "low" and <1% "negative."
- What is CPS? It is the sum of PD-L1-stained tumor cells, lymphocytes and macrophages, divided by the number of viable tumor cells and multiplied by 100. It has no unit and is capped at 100. It is used in gastric, esophageal, head and neck, cervical and triple-negative breast cancer.
- What does the staining rate change? As the rate rises, the benefit of immunotherapy generally becomes clearer. In lung cancer, for example, pembrolizumab extends median survival by about 8 months at TPS ≥50%, whereas its contribution on its own is limited at TPS 1–49%. In gastric cancer, immunotherapy has been approved in the US since 2025 only for patients with PD-L1 ≥1.
- Is the result definitive? No. The site and size of the biopsy, the antibody used, previous treatments and the reviewing pathologist can all change the result. Some PD-L1-negative patients also benefit; the decision is made together with other biomarkers.
Why does this matter?
Immune checkpoint inhibitors that target PD-1 and PD-L1 have changed the treatment of many cancers over the past decade, including lung, gastric, esophageal, head and neck, breast, cervical and bladder cancer. These drugs do not work equally well in every patient, however, and in some they can cause significant immune-related side effects (side effects of immunotherapy). PD-L1 staining is the most widely used test for predicting in advance which patients are likely to benefit most.
In many cancers, the PD-L1 result now directly shapes the choice of treatment: it affects whether immunotherapy is given alone, with chemotherapy or not at all, whether the drug falls within its approved indication and whether reimbursement criteria in Türkiye are met. The fact that the same report line can count as "high" in one cancer and "insufficient" in another can be confusing for patients and their families. Knowing what the numbers in your report show makes it easier to discuss your treatment options with your doctor in an informed way and, when needed, to ask for a second opinion.
What do CPS and TPS mean in PD-L1 testing?
TPS is the proportion of PD-L1-stained tumor cells among all viable tumor cells and is written as a percentage. CPS is obtained by dividing the sum of stained tumor cells, lymphocytes and macrophages by the number of viable tumor cells and multiplying by 100; its maximum is 100. In general, the higher the value, the greater the likelihood that immunotherapy will be of benefit.
What is PD-L1, and why is it measured?
The T cells of our immune system can recognize and eliminate abnormal cells. To keep this attack from harming healthy tissue, the body has checkpoints that act as "brakes." One of them is the PD-1 receptor on the surface of T cells. Some tumor cells and the immune cells around them carry a protein called PD-L1 on their surface. When PD-L1 binds to PD-1, the T cell stops, and the tumor can hide from the immune system.
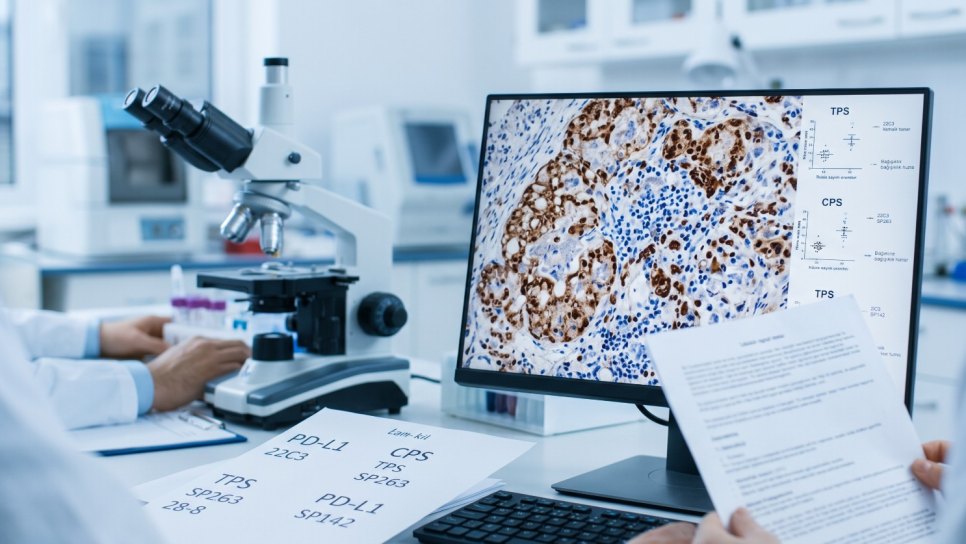
Pembrolizumab, nivolumab, tislelizumab, sintilimab, cemiplimab and dostarlimab bind to PD-1, while atezolizumab, durvalumab and avelumab bind to PD-L1, releasing this brake (nivolumab (Opdivo), immunotherapies and cancer vaccines). The PD-L1 test tries to measure how firmly this brake is "set" in the tumor. It is performed by applying a PD-L1-specific antibody to thin sections prepared from biopsy or surgical tissue; this is called immunohistochemistry (IHC). Under the microscope, the membranes of cells carrying PD-L1 appear brown.
Figure 1 · The PD-1 / PD-L1 brake and immunotherapy
With the brake on, and when the drug releases it
How is TPS calculated?
When calculating TPS (tumor proportion score), the pathologist looks only at viable tumor cells. Tumor cells with partial or complete brown membrane staining of any intensity are counted as "positive." The number of positive tumor cells is divided by the total number of viable tumor cells and multiplied by 100. For example, if 300 of 1,000 tumor cells are stained, the TPS is 30%. Immune cells, connective tissue and necrotic areas are not included in the calculation. For a reliable result, the sample must contain at least 100 viable tumor cells.
Figure 2 · Calculating TPS
Only tumor cells are counted
How is CPS calculated?
CPS (combined positive score) also takes into account the immune environment around the tumor. The numerator includes PD-L1-stained tumor cells, lymphocytes and macrophages together; the denominator is again viable tumor cells only. The result is multiplied by 100. Because immune cells are also in the numerator, the calculated value can exceed 100; in that case, the result is reported as 100. CPS is not a percentage but a unitless score. That is why "CPS 10," not "CPS 10%," is the correct way to write it.
In the same sample, CPS is never lower than TPS: if immune cells are stained, CPS can be markedly higher than TPS. In gastric, esophageal and head and neck cancers, much of the PD-L1 is found not on tumor cells but on the surrounding immune cells; this is why CPS is preferred in these cancers.
Figure 3 · TPS and CPS in the same sample
How does the result change when immune cells are counted?
| Score | What does it count? | How is it written? | Where is it used? |
|---|---|---|---|
| TPS | Stained tumor cells only | Percentage (0–100%) | Non-small cell lung cancer; some esophageal cancers for nivolumab |
| CPS | Stained tumor cells + lymphocytes + macrophages | Unitless score (0–100) | Gastric, esophageal, head and neck, cervical, triple-negative breast cancer |
| TC / IC | TC: tumor cells; IC: area occupied by immune cells in the tumor area | Percentage | SP142 assay for atezolizumab (e.g., lung cancer) |
| TAP | Area occupied by stained tumor and immune cells relative to the tumor area | Percentage | SP263 assay for tislelizumab (gastric and esophageal cancer) |
Which score and which cutoff in which cancer?
PD-L1 cutoffs are set according to the patient group in which each drug showed benefit in its own phase 3 trial. As a result, different scores and cutoffs may be used depending on the drug, even within the same cancer, and approvals in the US (FDA), Europe (EMA, the European Medicines Agency) and Türkiye may also differ. The diagram and table below summarize the most common situations.
Figure 4 · PD-L1 score by cancer type
Main settings in which TPS, CPS and TAP are used
| Cancer / setting | Score and cutoff (US) | Difference in Europe | Supporting trial |
|---|---|---|---|
| Lung (NSCLC), first line, single-agent immunotherapy | TPS ≥50% (pembrolizumab also TPS ≥1%) | Single-agent pembrolizumab only at TPS ≥50% | KEYNOTE-024, KEYNOTE-042 |
| Lung, chemotherapy + immunotherapy | Regardless of PD-L1 | Similar | KEYNOTE-189, KEYNOTE-407 |
| Head and neck, first line | CPS ≥1 | CPS ≥1 | KEYNOTE-048 |
| Gastric / gastroesophageal junction (HER2-negative) | PD-L1 ≥1 (since 2025) | Nivolumab CPS ≥5, pembrolizumab CPS ≥1 | CheckMate 649, KEYNOTE-859, RATIONALE-305 |
| Gastric (HER2-positive) | CPS ≥1 | CPS ≥1 | KEYNOTE-811 |
| Esophageal squamous cell carcinoma | PD-L1 ≥1 (since 2025) | Pembrolizumab CPS ≥10, nivolumab TPS ≥1% | KEYNOTE-590, CheckMate 648 |
| Triple-negative breast, metastatic | CPS ≥10 | CPS ≥10 | KEYNOTE-355 |
| Cervical, advanced stage | CPS ≥1 | CPS ≥1 | KEYNOTE-826 |
| Stage 3 lung, durvalumab after chemoradiotherapy | Regardless of PD-L1 | TPS ≥1% | PACIFIC |
The information summarized in the table is current as of October 2026; approvals may change over time. For licensing and reimbursement criteria in Türkiye, see the box "The situation in Türkiye" below.
Lung cancer: TPS and the 50% cutoff
In non-small cell lung cancer (NSCLC), PD-L1 is requested at diagnosis together with molecular tests (lung cancer). In the KEYNOTE-024 trial, single-agent first-line pembrolizumab in patients with TPS ≥50% raised the response rate from 27.8% to 44.8% compared with chemotherapy and clearly prolonged survival. At five years, 31.9% of patients in the pembrolizumab arm and 16.3% of those in the chemotherapy arm were alive. Cemiplimab and atezolizumab are also drugs that can be used alone in high PD-L1 (planning immunotherapy in lung cancer).
Long-term outcome at high PD-L1: share of patients alive at 5 years
Phase 3 KEYNOTE-024 trial; advanced lung cancer with TPS ≥50%, first line. 5-year overall survival, %.
In relative terms, the risk of loss of life fell by about 38% (hazard ratio 0.62); in absolute terms, about 16 more patients out of every 100 were alive after 5 years. The difference persisted even though many patients in the chemotherapy arm were later able to cross over to immunotherapy.
The KEYNOTE-042 trial, in turn, tested lowering the cutoff to 1%. In the overall TPS ≥1% group, pembrolizumab prolonged survival; however, a detailed analysis showed that the benefit came largely from patients with TPS ≥50%. In patients with TPS between 1% and 49%, the advantage of single-agent pembrolizumab over chemotherapy was not clear. Today, patients in this group usually receive immunotherapy together with chemotherapy; for PD-L1-negative patients, chemoimmunotherapy or dual immunotherapy (nivolumab + ipilimumab) are also options.
In lung cancer, the higher the PD-L1, the clearer the contribution of immunotherapy
Phase 3 KEYNOTE-042 trial; advanced non-small cell lung cancer, first-line pembrolizumab vs chemotherapy. Median overall survival, months.
In the TPS ≥50% group, pembrolizumab extended median survival by about 8 months (hazard ratio 0.69). In the TPS 1–49% group, the difference was about 1 month and was not statistically significant (hazard ratio 0.92; exploratory analysis). This is why, today, immunotherapy at low PD-L1 is usually given together with chemotherapy.
There is another important caveat in lung cancer: if a driver genetic alteration such as EGFR, ALK or ROS1 is present, targeted drugs are the first choice even when PD-L1 is high. Immunotherapy is less effective in these patients, and the risk of side effects can increase when it is used in sequence with certain targeted drugs. For this reason, the PD-L1 result is assessed together with next-generation sequencing (NGS) results.
Figure 5 · Decision path by PD-L1 in lung cancer
Driver alteration first, then TPS
Head and neck cancers
CPS came into use in recurrent or metastatic cancers of the mouth, pharynx and larynx with the KEYNOTE-048 trial. Single-agent pembrolizumab extended median survival from 10.7 to 14.9 months in patients with CPS ≥20, and from 10.3 to 12.3 months in those with CPS ≥1. In the small group with CPS below 1, no benefit of single-agent pembrolizumab was shown. Thus, single-agent immunotherapy becomes a stronger option as CPS rises, whereas at low CPS, combining it with chemotherapy is preferred (treatment of head and neck cancer, new approaches in PD-L1-negative head and neck cancer).
Gastric and esophageal cancer
In HER2-negative advanced gastric cancer, adding immunotherapy to chemotherapy prolonged survival in the CheckMate 649 (nivolumab), KEYNOTE-859 (pembrolizumab) and RATIONALE-305 (tislelizumab) trials. However, the benefit became more pronounced as PD-L1 rose; no meaningful benefit was shown in patients with PD-L1 below 1. In September 2024, the advisory committee of the US Food and Drug Administration (FDA), the Oncologic Drugs Advisory Committee (ODAC), concluded that the benefit-risk balance in this group was not favorable, and in 2025, approvals were restricted to patients with PD-L1 ≥1. The same restriction was applied to squamous cell carcinoma of the esophagus. Because about 80–90% of gastric cancers have PD-L1 ≥1, most patients remain eligible for immunotherapy (immunotherapy in advanced gastric and esophageal cancer, ESMO 2026 gastric and esophageal cancer guideline).
In gastric cancer, the benefit grows as PD-L1 rises
Phase 3 KEYNOTE-859 trial; HER2-negative advanced gastric and gastroesophageal junction cancer, pembrolizumab + chemotherapy. Relative reduction in the risk of loss of life, %.
Hazard ratios were 0.78, 0.74 and 0.65, respectively. Median survival increased from 11.5 to 12.9 months in all patients and from 11.8 to 15.7 months in the CPS ≥10 group. No clear benefit was shown in the small group with PD-L1 below 1; this is why US approvals were restricted to PD-L1 ≥1.
Triple-negative breast cancer
In metastatic triple-negative breast cancer, the KEYNOTE-355 trial is one of the clearest examples of how much the CPS cutoff matters. In patients with CPS ≥10, adding pembrolizumab to chemotherapy extended median survival from 16.1 to 23.0 months; across the whole CPS ≥1 group, the difference was limited to 1.6 months and was not significant. For this reason, the approval is limited to patients with CPS ≥10. By contrast, in early-stage (preoperative) triple-negative breast cancer, pembrolizumab is used regardless of PD-L1 (early-stage triple-negative breast cancer, sacituzumab govitecan).
The CPS cutoff in breast cancer: 1 or 10?
Phase 3 KEYNOTE-355 trial; metastatic triple-negative breast cancer, first-line pembrolizumab + chemotherapy vs chemotherapy. Median overall survival, months.
In the CPS ≥10 group, median survival was extended by 7 months (hazard ratio 0.73). In the CPS ≥1 group, the difference was limited to 1.6 months and was not significant (hazard ratio 0.86). This is why the approval is for patients with CPS ≥10.
Cervical, bladder and other cancers
In advanced cervical cancer, based on the KEYNOTE-826 trial, pembrolizumab is added to chemotherapy (with or without bevacizumab) in patients with CPS ≥1 (bevacizumab in cervical cancer). In bladder cancer, a PD-L1 cutoff used to be required for patients who could not receive cisplatin, but today the first-line combination of enfortumab vedotin and pembrolizumab is used regardless of PD-L1 (bladder cancer). In melanoma, kidney cancer and MSI-H/dMMR tumors, the decision on immunotherapy is made without regard to PD-L1.
Same tumor, different test: antibodies and platforms
PD-L1 tests are not all the same. Each drug was developed with a specific antibody and staining instrument in its own clinical trial. This is why your report states the "clone" of the test (e.g., 22C3, 28-8, SP263, SP142). Comparison studies (the Blueprint project) showed that 22C3, 28-8 and SP263 stain tumor cells at similar rates, whereas SP142 stains tumor cells markedly less. As a result, a result that is "low" with SP142 may be "high" with another test.
| Antibody (clone) | Drug it was developed for | Main score | Note |
|---|---|---|---|
| 22C3 | Pembrolizumab | TPS, CPS | The most widely used test in Türkiye and worldwide |
| 28-8 | Nivolumab | TPS, CPS | Largely concordant with 22C3 |
| SP263 | Durvalumab, tislelizumab | TPS, TAP | Gives results close to 22C3 on tumor cells |
| SP142 | Atezolizumab | TC, IC | Stains tumor cells less; should not be used interchangeably |
Some laboratories use tests they have developed and validated themselves (laboratory-developed tests) instead of an approved test kit. When properly validated, these tests can give reliable results; however, the report should state clearly which method was used.
What does the staining rate change?
PD-L1 is not a "present or absent" test but a continuous measurement. The general rule is this: as the staining rate rises, the likelihood of responding to immunotherapy and the gain in survival increase. This relationship is not absolute, however:
- High PD-L1 is not a guarantee: About half of patients with lung cancer and TPS ≥50% do not respond to single-agent immunotherapy.
- Low or negative PD-L1 is not a reason to lose hope: Some PD-L1-negative patients also benefit, especially when immunotherapy is given with chemotherapy or when other features such as MSI-H or high TMB are present.
- The two sides of a cutoff are not very different: There is no biological chasm between a TPS of 49% and 51%. Cutoffs are boundary values chosen to separate patient groups in clinical trials.
- Cancer type matters: The same CPS value may be sufficient for approval in one cancer but insufficient in another.
What affects the result?
PD-L1 is not distributed evenly within a tumor. One area may show intense staining, while a few millimeters away there may be none at all. A small needle biopsy may not reflect the tumor as a whole. In addition, PD-L1 can change over time and with treatment: chemotherapy, radiotherapy and targeted drugs can increase or decrease staining. There may also be differences between the primary tumor and metastases (types of biopsy).
Figure 6 · Intratumoral heterogeneity
The biopsy site can change the PD-L1 result
Figure 7 · Factors affecting the PD-L1 result
Tumor, sample, test and assessment
The reviewing pathologist can also affect the result. For TPS, agreement between pathologists is generally good, especially at the 1% and 50% cutoffs. For CPS, however, because immune cells are harder to distinguish, agreement can drop markedly at low values (around CPS 1). For this reason, when a borderline result would change the treatment decision, asking for a second review by an experienced pathology team is a reasonable step. AI-assisted image analysis methods are also being developed to reduce this variability (predicting immunotherapy response with AI).
How should you read your PD-L1 report?
A good PD-L1 report does not just give a number; it also explains how that number was obtained. You can check whether your report includes the following information:
| What you see in the report | What does it mean? |
|---|---|
| "PD-L1 (22C3 pharmDx, Dako Autostainer Link 48)" | The antibody and instrument used; shows which drug's trial the result can be compared with |
| "TPS: 60%" or "TPS ≥50%" | 60% of tumor cells are stained; "high PD-L1" in lung cancer |
| "TPS: 1–49%" or "low expression" | Positive but not high; treatment is usually planned as a combination |
| "TPS <1%" or "negative" | No meaningful staining of tumor cells |
| "CPS: 15" | A score of 15 based on tumor and immune cells combined; it exceeds the CPS ≥1 and ≥10 cutoffs |
| "Number of viable tumor cells ≥100" | The sample is adequate for assessment |
| "Insufficient material" or "not evaluable" | The result is not reliable; a new sample or another block may be needed |
| "Positive and negative controls appropriate" | Shows that the staining worked correctly from a technical standpoint |
If your report says only "PD-L1 positive," it is important to ask which score and which cutoff were used. Because the same tissue can have a TPS of 5% and a CPS of 20, the result cannot be interpreted correctly without knowing the type of score. For other concepts in pathology reports, see our guides on Ki-67 and surgical margins.
Is PD-L1 enough on its own? Other biomarkers
PD-L1 is only one of the biomarkers that predict response to immunotherapy. Other markers are also taken into account when making a decision:
- MSI-H / dMMR: Tumors with a defective DNA repair system can respond very well to immunotherapy regardless of PD-L1 (dostarlimab in dMMR gastric and esophageal cancer).
- Tumor mutational burden (TMB): Tumors carrying many mutations may be recognized more easily by the immune system; TMB and PD-L1 are largely independent of each other (pembrolizumab in TMB-high tumors).
- Driver genetic alterations: Alterations such as EGFR and ALK take precedence over immunotherapy in lung cancer (the genetic test report and ESCAT).
- Virus-associated tumors: In some tumors associated with HPV or EBV, the immune environment is different.
- New approaches: The density of immune cells surrounding the tumor, gene expression signatures and AI-based models are under investigation.
Questions you can ask your doctor
- Has my PD-L1 test been done? With which antibody (22C3, 28-8, SP263, SP142) and which score (TPS, CPS, TAP) was it assessed?
- For my cancer type and the recommended drug, is my result above or below the relevant cutoff?
- Does this result change whether immunotherapy is given alone or together with chemotherapy?
- On which sample was the test done (primary tumor or metastasis)? Was the sample adequate?
- If my result is close to the cutoff, would it make sense to repeat the test on another block or a new sample?
- Have my MSI, TMB and genetic tests also been done? How do they affect the decision?
- "If I am PD-L1-negative, immunotherapy will not work for me at all." No. In many cancers, PD-L1-negative patients can also benefit from immunotherapy, especially when it is combined with chemotherapy; in situations such as MSI-H, PD-L1 is not checked at all.
- "If PD-L1 is high, the treatment is certain to work." No. High PD-L1 increases the likelihood of response but does not guarantee it; a substantial proportion of patients with high PD-L1 do not respond.
- "CPS 10 means 10%." No. CPS is not a percentage but a unitless score; it does not mean that only 10% of tumor cells are stained.
- "PD-L1 is checked with a blood test." No. The standard PD-L1 test is performed on tumor tissue; measuring PD-L1 in the blood is not currently used to make treatment decisions.
- "Once it has been checked, the result never changes." It can change. Because of intratumoral heterogeneity, metastases and treatments, different results can be obtained at different times and from different samples.
- In Türkiye, PD-L1 testing (mostly 22C3, SP263 at some centers) is available at university hospitals, training and research hospitals and private pathology laboratories. Reporting formats can vary from center to center; if your report does not state the score type and antibody, you can ask your doctor for them.
- Drug licensing in Türkiye (by TİTCK, the Turkish Medicines and Medical Devices Agency) mostly follows European approvals; as a result, some cutoffs may differ from those in the US.
- Reimbursement by SGK (the Social Security Institution) depends, for many indications, on the PD-L1 result and on the conditions of a health board report. For current criteria, see our article on immunotherapy reimbursement criteria.
- In situations outside reimbursement coverage, off-label use approval or importing the drug from abroad may come into play; a complete PD-L1 report is important in this process.
Frequently Asked Questions
- What is the difference between TPS and CPS in PD-L1 testing?
- TPS is simply the proportion of PD-L1-stained tumor cells among all viable tumor cells and is written as a percentage. CPS adds lymphocytes and macrophages to the stained tumor cells, divides by the number of viable tumor cells and multiplies by 100. CPS is unitless with a maximum of 100; in the same tissue, it can come out higher than TPS.
- What PD-L1 percentage is needed for immunotherapy?
- It depends on the cancer type and the drug. In lung cancer, TPS ≥50% is sufficient for single-agent immunotherapy; at lower values, immunotherapy is usually given with chemotherapy. In gastric, esophageal, head and neck and cervical cancer, CPS ≥1 is required, and in metastatic triple-negative breast cancer, CPS ≥10.
- Can I receive immunotherapy if my PD-L1 is negative?
- In some situations, yes. In lung cancer, immunotherapy combined with chemotherapy can be used regardless of PD-L1; in MSI-H/dMMR tumors and melanoma, PD-L1 is not considered. However, in some cancers, such as gastric and esophageal cancer, if PD-L1 is below 1, the benefit is limited and treatment may fall outside the approved indication.
- Should the PD-L1 test be repeated?
- Not always. However, if the sample was inadequate, the result is very close to the cutoff, the test was done years ago or on a different tumor site, or the result does not fit the clinical picture, you can discuss with your doctor whether to repeat the test on a new biopsy or another block.
Glossary
- PD-1
- A checkpoint receptor on the surface of T cells that puts the brakes on the T cell when bound.
- PD-L1
- A protein that can be found on tumor and immune cells and suppresses the immune response by binding to PD-1.
- Immunohistochemistry (IHC)
- Visualizing a protein in a tissue section under the microscope by staining it with specific antibodies.
- TPS (tumor proportion score)
- The percentage of PD-L1-stained tumor cells among all viable tumor cells.
- CPS (combined positive score)
- The sum of stained tumor cells, lymphocytes and macrophages, divided by the number of viable tumor cells and multiplied by 100; maximum 100.
- TAP score
- The area occupied by stained tumor and immune cells relative to the tumor area; used for tislelizumab.
- Companion diagnostic
- A test approved together with a drug to determine which patients the drug should be used in.
- Clone
- The name of the antibody used in a PD-L1 test (e.g., 22C3, 28-8, SP263, SP142).
- Immune checkpoint inhibitor
- A drug that strengthens the immune system's response to the tumor by blocking brakes such as PD-1, PD-L1 or CTLA-4.
- Intratumoral heterogeneity
- Differences in cell characteristics and staining between different areas of the same tumor.
DROZDOGAN Academy Commentary
PD-L1 is the most widely used yet most debated biomarker of the immunotherapy era. Read correctly, it makes choosing treatment easier; used as a simple "yes/no" test, it can be misleading.
⚡ Why it matters
In lung, gastric, esophageal, head and neck, cervical and breast cancer, who receives immunotherapy, how and under which reimbursement criteria now depends directly on PD-L1 cutoffs. The 2025 US restriction once again showed how much these cutoffs matter.
✅ Strengths
An inexpensive, widely available and fast tissue test. Large phase 3 trials have consistently shown that benefit increases as PD-L1 rises; in lung cancer with TPS ≥50%, the long-term survival gain has been confirmed with 5-year data.
⚠️ Limitations
Different antibodies, different scores and different cutoffs create confusion. Intratumoral heterogeneity, small biopsies and interobserver variability among pathologists, especially at low CPS values, can push the result to either side of the cutoff. Some PD-L1-negative patients also benefit.
🩺 In practice
We always assess PD-L1 using the score and cutoff specific to the cancer type, together with MSI, TMB and genetic test results. We ask for the antibody and score type to be stated in the report, and for results close to the cutoff or out of keeping with the clinical picture, we discuss reassessment or a new sample at the tumor board.
❓ Open questions
Will AI-assisted counting eliminate interobserver variability among pathologists? Will composite biomarkers that predict response better than PD-L1 (immune environment, gene signatures, circulating tumor DNA) become routine?
Bottom line: TPS counts only tumor cells, while CPS counts tumor and immune cells together. As the staining rate rises, the benefit of immunotherapy generally grows; but cutoffs vary by cancer type and drug, and PD-L1 is no guarantee of response. Review your report with your doctor, taking into account the score type, the antibody and your cancer type.
- This article was prepared in October 2026.
- The lung cancer data are based on the KEYNOTE-024 and KEYNOTE-042 trials, the head and neck data on KEYNOTE-048, the breast cancer data on KEYNOTE-355, the gastric cancer data on KEYNOTE-859 and CheckMate 649, and the cervical data on KEYNOTE-826; the test comparisons are based on the Blueprint project, and the 2024–2025 US restriction on the FDA advisory committee meeting and related news reports.
- Cutoffs and approvals differ by country and may change over time; the table is a general summary as of October 2026.
- The illustrations are simplified; many more cells are counted in a real assessment. The Academy commentary is our own.
- This article is not medical advice; review your PD-L1 result together with your treatment team.
References
- Reck M, Rodríguez-Abreu D, Robinson AG, et al. Five-year outcomes with pembrolizumab versus chemotherapy for metastatic non-small-cell lung cancer with PD-L1 tumor proportion score ≥50%. J Clin Oncol 2021;39:2339-2349. doi:10.1200/JCO.21.00174
- Mok TSK, Wu YL, Kudaba I, et al. Pembrolizumab versus chemotherapy for previously untreated, PD-L1-expressing, locally advanced or metastatic non-small-cell lung cancer (KEYNOTE-042). Lancet 2019;393:1819-1830. doi:10.1016/S0140-6736(18)32409-7
- Burtness B, Harrington KJ, Greil R, et al. Pembrolizumab alone or with chemotherapy versus cetuximab with chemotherapy for recurrent or metastatic squamous cell carcinoma of the head and neck (KEYNOTE-048). Lancet 2019;394:1915-1928. doi:10.1016/S0140-6736(19)32591-7
- Cortes J, Rugo HS, Cescon DW, et al. Pembrolizumab plus chemotherapy in advanced triple-negative breast cancer. N Engl J Med 2022;387:217-226. doi:10.1056/NEJMoa2202809
- Rha SY, Oh DY, Yañez P, et al. Pembrolizumab plus chemotherapy versus placebo plus chemotherapy for HER2-negative advanced gastric cancer (KEYNOTE-859). Lancet Oncol 2023;24:1181-1195. doi:10.1016/S1470-2045(23)00515-6
- Janjigian YY, Shitara K, Moehler M, et al. First-line nivolumab plus chemotherapy versus chemotherapy alone for advanced gastric, gastro-oesophageal junction, and oesophageal adenocarcinoma (CheckMate 649). Lancet 2021;398:27-40. doi:10.1016/S0140-6736(21)00797-2
- Colombo N, Dubot C, Lorusso D, et al. Pembrolizumab for persistent, recurrent, or metastatic cervical cancer. N Engl J Med 2021;385:1856-1867. doi:10.1056/NEJMoa2112435
- Tsao MS, Kerr KM, Kockx M, et al. PD-L1 immunohistochemistry comparability study in real-life clinical samples: results of Blueprint phase 2 project. J Thorac Oncol 2018;13:1302-1311. doi:10.1016/j.jtho.2018.05.013
- U.S. Food and Drug Administration. Oncologic Drugs Advisory Committee meeting: immune checkpoint inhibitors in HER2-negative gastric/GEJ adenocarcinoma and esophageal squamous cell carcinoma. September 26, 2024. fda.gov
- Targeted Oncology. Checkpoint inhibitors in advanced upper GI cancers after 2024 FDA shift. March 25, 2026. targetedonc.com
Was this article helpful?
Your feedback helps us improve our content.